
Understanding Hypertension: Risk Factors, Mechanisms, and Long-Term Implications

Key Takeaways
What hypertension actually means
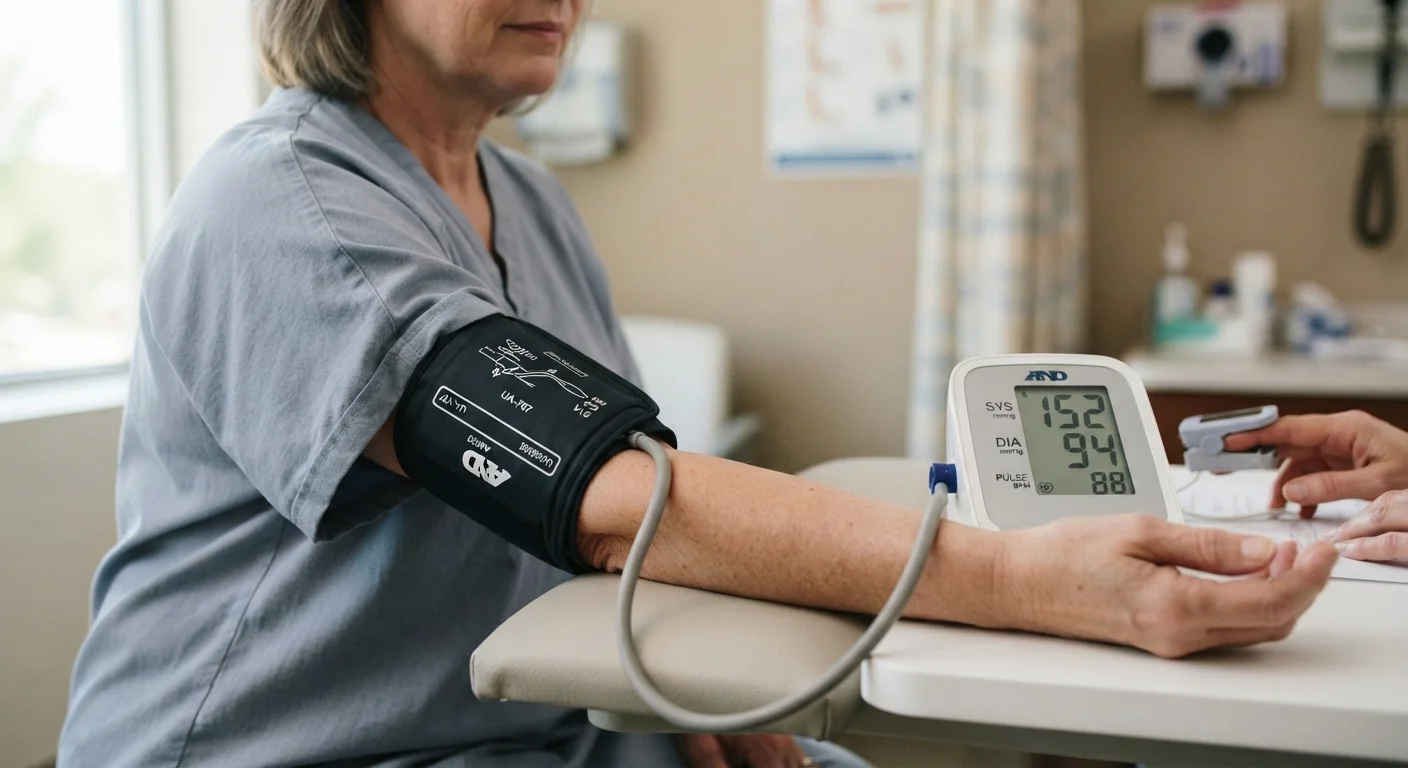
Blood pressure is the force blood exerts against artery walls as the heart pumps. Two numbers describe it: systolic pressure (the force during a heartbeat) and diastolic pressure (the force between beats), both measured in millimeters of mercury (mmHg). The American College of Cardiology and the American Heart Association define hypertension as a sustained reading at or above 130/80 mmHg.
The word "sustained" matters. Blood pressure fluctuates constantly in response to activity, stress, sleep, and even posture. A single elevated reading does not confirm hypertension. Clinicians look for consistently elevated values across multiple measurements, often taken at different visits or with ambulatory monitoring worn over 24 hours.
Roughly 47% of U.S. adults meet the current diagnostic threshold, according to data published by the Centers for Disease Control and Prevention. Many have no symptoms at all, which is why hypertension is sometimes called a silent condition. For a broader starting point on how blood pressure works, see our complete beginner's guide to heart and blood pressure health.
47%
U.S. adults with hypertension
According to data published by the Centers for Disease Control and Prevention, nearly half of American adults meet the current diagnostic threshold.
130/80 mmHg
Current U.S. diagnostic threshold
The American College of Cardiology and American Heart Association adopted this lower threshold in 2017 guidelines, expanding the number of adults classified as hypertensive.
2 to 8 mmHg
Systolic reduction from sodium restriction
Reducing dietary sodium to under 2,300 mg per day produces this approximate systolic blood pressure drop in most adults, with larger effects in sodium-sensitive individuals.
The main risk factors
Hypertension rarely has one cause. In the majority of cases, classified as primary or essential hypertension, the condition reflects a combination of genetic predisposition and environmental exposures accumulated over years.
Modifiable factors
Excess body weight increases the workload on the heart and raises systemic vascular resistance. Dietary sodium drives fluid retention, expanding blood volume. Physical inactivity allows the cardiovascular system to become less efficient. Excessive alcohol consumption raises blood pressure through several pathways, including activation of the sympathetic nervous system. Chronic stress and poor sleep both elevate cortisol and catecholamines, hormones that constrict blood vessels and increase heart rate. Our article on sleep, stress, and blood pressure covers these hormonal pathways in depth.
Many people are also unaware of how everyday habits quietly compound risk. Certain common behaviors push blood pressure upward through mechanisms that are well-documented but easy to overlook.
Non-modifiable factors
Age is the strongest non-modifiable predictor. Arteries stiffen naturally with age, raising systolic pressure in particular. Family history of hypertension or cardiovascular disease roughly doubles individual risk. Black adults in the United States experience higher rates of hypertension and earlier onset compared with other racial groups, a disparity driven by a combination of genetic, socioeconomic, and structural factors.
How elevated pressure damages organs over time
Persistent high pressure injures the inner lining of arteries, called the endothelium. Once that lining is damaged, it becomes more permeable to lipids, which contributes to atherosclerotic plaque formation. Narrower, stiffer arteries require even higher pressure to maintain blood flow, creating a self-reinforcing cycle.
Heart
The heart must work harder to pump against elevated resistance. Over time the left ventricle thickens, a condition called left ventricular hypertrophy. Thickened muscle is less flexible, increases oxygen demand, and raises the risk of heart failure and arrhythmias.
Brain
High pressure strains cerebral blood vessels. Small vessel disease in the brain reduces white matter integrity and contributes to cognitive decline. The risk of both ischemic stroke (from blockage) and hemorrhagic stroke (from vessel rupture) rises substantially with sustained hypertension.
Kidneys
The kidneys filter blood through tiny capillaries that are vulnerable to pressure-related damage. Hypertension accelerates loss of kidney function and is a leading cause of chronic kidney disease in the United States. Damaged kidneys, in turn, retain more sodium and water, which raises blood pressure further.
Eyes
Hypertensive retinopathy describes damage to the blood vessels supplying the retina. Prolonged uncontrolled hypertension can cause vision changes and, in severe cases, vision loss.
The role of hormones and the kidneys
Blood pressure regulation is not purely mechanical. A hormonal system called the renin-angiotensin-aldosterone system (RAAS) adjusts pressure in response to blood volume and sodium levels. When blood pressure or sodium drops, the kidneys release renin, which triggers a chain reaction producing angiotensin II, a potent vessel-constrictor. Angiotensin II also stimulates aldosterone release from the adrenal glands, prompting the kidneys to retain sodium and water.
In hypertension, this system can become overactive or dysregulated, sustaining elevated pressure even when volume is adequate. Several antihypertensive drug classes work specifically by blocking components of the RAAS. The broader field of hormonal balance is relevant here because cortisol, thyroid hormones, and insulin resistance all interact with blood pressure regulation in ways that clinicians consider during workup.
The liver also processes aldosterone and other hormones; liver dysfunction can impair this clearance. For context on how organ systems interconnect, see our resource on liver health and daily habits.
What the evidence says about management
Clinical guidelines consistently support lifestyle modification as a first-line approach for elevated blood pressure in the absence of high cardiovascular risk. The evidence for specific interventions is well-established.
- Reducing dietary sodium to under 2,300 mg per day lowers systolic pressure by approximately 2 to 8 mmHg in most adults, with larger effects in those who are sodium-sensitive.
- The DASH dietary pattern (high in vegetables, fruits, whole grains, and low-fat dairy; low in saturated fat and sodium) produces clinically meaningful blood pressure reductions in controlled trials.
- Aerobic exercise performed on most days of the week is associated with systolic reductions in the range of 4 to 9 mmHg, based on data reviewed by major cardiology organizations.
- Limiting alcohol to moderate levels, as defined by current U.S. dietary guidelines, is associated with lower blood pressure compared with heavier consumption.
- Weight loss in adults with excess weight reduces blood pressure, with roughly 1 mmHg of systolic reduction per kilogram lost on average.
Many people with hypertension require antihypertensive medication in addition to lifestyle changes, particularly when blood pressure is significantly elevated or cardiovascular risk is high. Several drug classes are available, and decisions about which agent to use are individualized. This article does not advise starting, stopping, or changing any medication.
Common myths about what controls blood pressure can lead people to underestimate their risk or skip appropriate care. Our article on widespread hypertension misconceptions addresses the most consequential ones.
When to involve a healthcare provider
Anyone who records a blood pressure reading at or above 130/80 mmHg on multiple occasions should discuss those readings with a clinician. A single high reading at home is not a reason for alarm, but a pattern warrants evaluation.
Certain situations call for prompt medical attention. A reading above 180/120 mmHg, particularly when accompanied by chest pain, severe headache, shortness of breath, or vision changes, requires emergency care. This is sometimes described as a hypertensive crisis and is a medical emergency.
People with diabetes, chronic kidney disease, or established cardiovascular disease generally have lower treatment thresholds because their overall risk profile is higher. Older adults and people in special populations, including pregnant individuals, require individualized guidance from a qualified provider rather than general advice.
Monitoring at home with a validated arm cuff can complement clinical readings, but home monitors should be calibrated and used correctly to be meaningful. A clinician can advise on technique and help interpret the pattern of results.
This article is for informational purposes only and is not a substitute for professional medical advice, diagnosis, or treatment. Always consult a qualified healthcare provider with questions about your blood pressure or cardiovascular health.